
Hernia Surgery in Dubai — Laparoscopic and Open Repair
Hernia surgery in Dubai is carried out by Prof. Dr Antonio Privitera, Consultant General and Colorectal Surgeon, using laparoscopic or open repair for groin and abdominal wall hernias. He sees patients at Medcare Royal Speciality Hospital, Clemenceau Medical Center, Aster Hospital Al Qusais, Medcare Discovery Gardens and Medcare JVC. To book, call or WhatsApp +971 55 318 8469 and the secretary will match the clinic to your insurance.
Fellowship-trained: Mayo Clinic (USA) · United Kingdom · South Korea — Associate Professor, UAE University
Insurance: I consult at seven clinics across four hospital groups, so most major insurers are covered at one of them. See insurance plans by clinic.
Hernias can be acquired or congenital depending on whether they develop over the years or they are present at birth. Dr Antonio is a consultant general and colorectal surgeon performing hernia surgery in Dubai and Abu Dhabi.
Booking: call +971 55 318 8469 or message on WhatsApp. The secretary will book you into the clinic that suits your insurance and how soon you need to be seen.
Dubai clinics: Medcare Royal, Al Qusais · Medcare Discovery Gardens · Medcare Medical Centre JVC, Circle Mall · Aster Hospital, Al Qusais · Clemenceau Medical Center.
Scope of practice: Prof. Privitera operates on abdominal wall and groin hernias only — inguinal, femoral, umbilical, para-umbilical, epigastric, incisional, ventral, spigelian and sports hernia. Hernias of the chest wall and upper digestive tract fall outside this practice and are not treated here.
The inguinal hernia is the most common type and has features that set it apart from the others. Our full explanation of inguinal hernia covers the symptoms, the repair and the recovery.
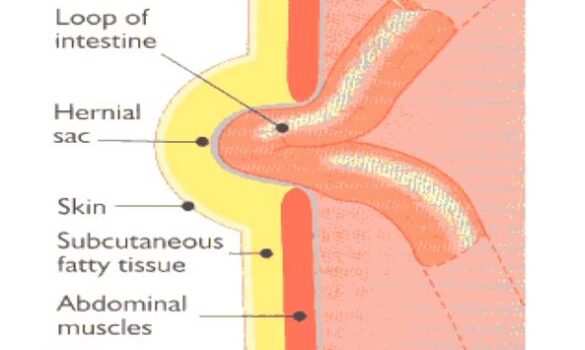
Types of Hernia We Repair
Predisposing factors to abdominal wall hernias are those that produce an increase in intra-abdominal pressure such as straining, heavy lifting, obesity, ascites, chronic cough, and multiple pregnancies. Also, there may be a weakness of the abdominal wall caused by aging, chronic illness, and defects in the metabolism of collagen and extracellular matrix.
Inguinal Hernia
The most common type, occurring in the groin where the abdominal wall is naturally weaker. More common in men, but can affect anyone.
Read more: inguinal hernia — all you need to know, or read about inguinal hernia surgery in Dubai and Abu Dhabi.
Femoral Hernia
Femoral hernias are more common in females and develop through the femoral canal, a space that is bounded laterally by the femoral vein, medially by the lacunar ligament, superiorly by the inguinal ligament, and posteriorly by Cooper’s ligament. They have a higher incidence of incarceration and strangulation.
Epigastric Hernia
Epigastric hernias are upper abdominal hernias that have usually a small defect and develop along the midline raphe. Most of the time the content of the hernia is pre-peritoneal fat. More rarely, omentum or part of upper abdominal organs can be found in it.
Incisional Hernia
Develops at the site of a previous surgical scar, where the abdominal wall has been weakened by the earlier operation.
Ventral Hernia
A general term for hernias occurring anywhere on the front of the abdomen, not limited to the umbilicus or a previous incision.
Read more: umbilical and ventral hernia repair.
Sports Hernia
A strain or tear in the soft tissue of the lower abdomen or groin, common in athletes, though it is not a true hernia in the classic sense.
Para-Umbilical Hernia
Occurs near the belly button, where the abdominal wall closes after birth. Common in adults, especially after pregnancy or weight gain.
Other less commonly encountered abdominal wall hernias include:
- Spigelian Hernia
- Lumbar Hernia
- Obturator Hernia
When a Hernia Is an Emergency
Hernias may cause pain that is exacerbated by increases of the abdominal pressure (cough, heavy lifting, straining on passing motion). The diagnosis of a hernia is mainly based on clinical examination.
Although it may be uncomfortable, introflecting the scrotal skin into the inguinal canal with the finger is the best way to appreciate an inguinal hernia as the full extent of the posterior wall of the inguinal canal can be assessed. Radiological imaging, e.g.
ultrasound scan, can be helpful in doubtful cases. A CT scan may be used in obese patients, in cases of emergency or to plan surgical treatment in very large hernias especially those following surgical procedures (incisional).
Acquired hernias can never resolve spontaneously and surgery is the only treatment to address a patient’s symptoms and to avoid the possibility of complications requiring surgical intervention. However, some hernias are more prone to complications than others. Femoral hernias have a high complication rate as the defect is small and mainly bounded by aponeurotic rigid structures. Direct inguinal hernias are incarcerated or strangulate very rarely.with
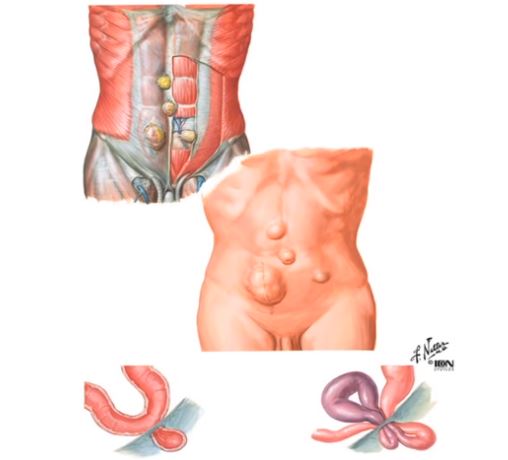
Complications of hernias include irreducibility, obstruction, and strangulation. When a hernia becomes irreducible, the hernia sac with its content cannot be pushed back into the abdominal cavity.
This is usually caused by adhesions of the sac with the surrounding structures or between the sac and its content. Hernias with a small defect are more likely to become irreducible. Intestinal hernia content may be complicated by bowel obstruction presenting with abdominal pain, distension, obstipation, nausea, and vomiting.
If the blood supply to the content becomes impaired, strangulation ensues and this may lead to gangrene and perforation. This is a life-threatening condition and requires emergency surgery.
A hernia becomes an emergency when it strangulates — the bulge becomes hard, very painful and cannot be pushed back, sometimes with vomiting or fever. This needs immediate hospital assessment, not a scheduled clinic visit. If this describes you now, go to the nearest emergency department.
Open vs Laparoscopic Repair
Open Repair
A traditional single incision directly over the hernia. Often preferred for simple, small hernias or when previous abdominal surgery makes keyhole access difficult. Recovery time varies between patients and is discussed with you beforehand.
Laparoscopic Repair
Performed through 3-4 small incisions using a camera and specialized instruments. Smaller incisions are used, and return to normal activity is usually quicker than after open repair. Well suited to bilateral or recurrent hernias.
Minimally invasive surgery
Most elective and emergency hernia repairs can be performed using minimally invasive laparoscopic techniques. These approaches use smaller incisions than open surgery. Recovery varies from patient to patient. Open surgery remains appropriate in selected patients, depending on the type and complexity of the hernia and the individual clinical circumstances.
The choice is made with you after examination and, where needed, imaging.
Modern Mesh Repair, Honestly Explained
In general, the use of prosthetic materials (mesh) in hernia surgery is the standard treatment as it is associated with a low recurrence rate. Meshes can be placed over the musculoaponeurotic abdominal wall structures (on-lay repair), in-between them (inlay repair), or below them (sub-lay repair). Before the introduction of meshes, the recurrence rate of hernias was high. This is because when a suture only repair is performed, there are two risk factors for recurrence that must be considered.
One is the tissue tension created by closing the defect and the other the weakness of the aponeurotic structures that in itself is a predisposing factor for hernia formation. As regards inguinal hernias, Bassini’s repair was the first hernia surgery repair described in the literature and was revolutionary.
The concept of closing the defect in the posterior wall of the inguinal canal by approximating the conjoint tendon or the inferior margin of the internal oblique and transversus abdominis to the inguinal ligament represented a milestone. The main drawback of this kind of repair is the tension that is created that is the prime etiological factor for hernia recurrence. Other surgeons, e.g. Shouldice, developed techniques of suture repair that helped to distribute the tension in several layers and thus achieving low recurrence rates.
The Lichtenstein hernia mesh technique with the apposition of a mesh to cover the defect (without closing it) was again a milestone in hernia surgery and gave way to the widespread use of prosthetic materials and the introduction of a wide variety of techniques by other surgeons. The recurrence rate of Lichtenstein repair for inguinal hernia is less than 1%.
Most hernia repairs today use a lightweight synthetic mesh to reinforce the weakened area, significantly reducing the chance of recurrence compared to suture-only repair. We understand many patients have questions or concerns about mesh — including rare complications reported in some cases — and we’re happy to discuss these openly during your consultation, along with the alternatives available for your specific situation.
Read more: how hernia mesh is used, and its risks.
Your Day-Surgery Pathway and Recovery
Most hernia repairs are day-case surgery — you go home the same day. Return to work depends on the type of repair and the physical demands of your job, and desk-based work is usually resumed before heavy manual work. Your surgeon will advise you based on your own operation and recovery.
You’ll receive written wound-care instructions and a direct contact number for any questions, plus a follow-up visit within 1-2 weeks to confirm healing.
Why Choose Dr Privitera
Dr Antonio Privitera holds an MD and PhD with a specific research focus in hernia surgery, and has authored peer-reviewed publications in the field. Dr Privitera’s dedicated experience — built on fellowship training in advanced minimally invasive techniques — means every repair is tailored to the patient’s specific anatomy and hernia type, prioritizing both durability and comfort.
Hernia operations are very commonly performed in Dubai and Abu Dhabi by most surgeons. For complex or recurrent hernias, assessment by a surgeon with appropriate experience in hernia surgery is particularly important.
Dr Antonio is a consultant general and colorectal surgeon performing hernia surgery in Dubai and Abu Dhabi. He holds an MD and Ph.D. in hernias and he is the author of numerous peer-reviewed research in the field. He developed a novel plug-technique for the treatment of umbilical and a double-layer mesh technique for lumbar hernias. Together with Prof. Angelo Donati in Italy, he developed the “Calibrated inguinal hernia repair” that was presented in several national and international conferences. He also worked with Prof. Andrew Kingsnorth, former President of the European Hernia Society.
Prefer to read in Arabic? Read this guide in Arabic: العربية
Looking for a Hernia Doctor in Dubai & Abu Dhabi?
A proctology service not only for Hernia Surgery in Dubai and Abu Dhabi but also for many other diseases is currently available at major hospitals in the region. Specialist consultation is available by appointment.
Book an Appointment
FAQs About Hernia Surgery
No. Hernias do not heal on their own. Surgery is the definitive treatment, and repair is advised to prevent complications such as strangulation.
More on hernia treatment without surgery.Discomfort after hernia repair varies from patient to patient and is managed with pain relief. Laparoscopic repair uses smaller incisions than open surgery. Your surgical team will explain what to expect and how your pain will be controlled.
Return to work depends on the type of repair, the physical demands of your job and how your recovery progresses. Desk-based work is usually resumed before heavy manual work. Your surgeon will advise you based on your own operation and recovery.
Outcomes depend on the type of hernia, the technique used and individual patient factors. Recurrence after a well-performed mesh repair is uncommon, but no operation can guarantee a particular result. Your surgeon will discuss what is realistic in your case.
Laparoscopic repair uses smaller incisions than open surgery. Which approach is appropriate depends on the hernia, your general health and any previous surgery. Dr Antonio recommends the approach best suited to each patient.
References
Papers by Prof. Dr Antonio Privitera on this subject:
- Donati M, Gandolfo L, Privitera A, Brancato G, Donati A. Day hospital for incisional hernia repair: selection criteria. Acta Chir Belg. 2008;108(2):198-202. doi:10.1080/00015458.2008.11680202
- Privitera A, Brancato G, Donati M, Gandolfo L, Cavallaro G, Donati A. Plug-technique for small incisional hernia. Ann Ital Chir. 2003;74(6):701-4; discussion 704-5. PubMed 15206813
- Donati M, Gandolfo L, Privitera A, Cavallaro G, Brancato G. [Inguinal hernia recurrence after prosthetic repair: our experience]. Chir Ital. 2003;55(4):609-15. PubMed 12938613
- Donati M, Gandolfo L, Privitera A, Palmeri S, Brancato G. [Femoral hernioplasty with a mesh plug]. Chir Ital. 2005;57(4):449-55. PubMed 16060182
More on the publications page.

Selected articles on hernia
Hernia assessment is also available in Abu Dhabi — see hernia surgery in Abu Dhabi for the consultation and theatre arrangements there.
